Next to the cost of a filling, a quote for a crown can come as a shock. The gap mostly comes down to how a crown is made: it is a custom piece built in a dental laboratory to cover the whole tooth, usually over two visits, rather than a material placed directly into a cavity in one sitting. In the Sydney market a single crown typically costs $1,500 to $2,500, and the rest of this article explains what sits behind that figure.
Written by Dr James Tran, dentist at Lumi Dental.
Where a quote lands in the $1,500 to $2,500 range
That range is a general market figure for one crown on a natural tooth, not a fee from any particular practice. Several things push an individual quote up or down.
- The material. All-ceramic and zirconia crowns often sit towards the upper end. Metal-based crowns can be a little lower.
- The laboratory work. A front tooth that has to match its neighbours closely may need more hand finishing by the technician than a back molar.
- What the tooth needs first. A root canal, a post and core build-up or treatment of the gum around the tooth are charged separately. Root canal treatment alone typically costs about $1,000 for a front tooth and up to $3,000 for a molar.
- Sedation. If you need help to relax during treatment, that is usually an additional item.
Crowns on implants are a separate category, because the implant itself is part of the cost. A single implant with its crown typically runs $4,000 to $7,000 in the same market.
Why a filling sometimes is not enough
A filling relies on the tooth around it for strength. Once a large part of the tooth has gone, through decay, fracture or an old filling that keeps getting bigger, the remaining walls can be thin and prone to splitting. A crown covers the whole visible part of the tooth and holds it together under biting forces.
The situations where a crown is most often suggested are a back tooth after root canal treatment, a tooth with a large filling that has started to fail, a cracked tooth where the crack has not reached the root, and a tooth on top of a dental implant. Crowns are also used to rebuild a badly worn or broken front tooth when bonding or a veneer will not be strong enough.
There is a middle option. An onlay covers only the damaged part of the biting surface and keeps more of the natural tooth. For some teeth that is a better choice than a full crown, and for small breaks, composite bonding may be all that is needed. A dentist should be able to show you on a photo or X-ray why one option is being recommended over another.
How the main materials compare
| Material | Strengths | Things to weigh up |
|---|---|---|
| Glass ceramic, such as lithium disilicate | Natural translucency, a good match for front teeth, bonds well to the tooth | May not be the first choice for people who grind heavily |
| Zirconia | Very strong, suits back teeth and implants, no metal to show at the gum | Earlier layered versions were prone to chipping of the porcelain surface; solid zirconia avoids that layer |
| Porcelain fused to metal | Long track record, strong | A grey line can appear at the gum if it recedes; less natural looking than ceramics |
| Gold or other metal | Gentle on opposing teeth, can be made thin so less tooth is removed | Appearance rules it out for most visible teeth |
A large systematic review by Sailer and colleagues, published in Dental Materials in 2015, pooled 67 studies of single crowns. It estimated that 94.7% of metal-ceramic crowns were still in place after five years, and most types of all-ceramic crown performed similarly. The weaker feldspathic and silica-based ceramics did less well on back teeth, and the zirconia crowns studied, mostly the older layered kind, had more problems with the surface porcelain chipping. Materials have moved on since then, but the general lesson stands: the right material depends on the tooth, your bite and how visible it is. If a grey line around an older crown is your concern, our article on a black line at the gum next to a crown explains why it happens.

What you are paying for across the two visits
At the first appointment the tooth is numbed and shaped to make room for the crown. The dentist then records the shape with a digital scan or an impression and fits a temporary crown to protect the tooth in the meantime.
Between visits, the laboratory makes the crown. This is a large part of the cost: a dental technician designs and mills or presses the crown, then stains and glazes it to match your other teeth. We describe this step in more detail in inside the dental laboratory.
At the second appointment the temporary comes off, the fit, bite and colour of the new crown are checked, and it is cemented or bonded in place. Some practices mill crowns on site in a single visit. That can be convenient, but the choice of material should still be driven by the tooth.
Comfort during and after
The tooth is numbed with local anaesthetic, so the preparation should not hurt. Afterwards it is common for the tooth and gum to be a little tender for a day or two, and a tooth that was already inflamed may stay sensitive to cold for longer. Pain that is getting worse, or that is not settling, should be checked.
For people who find dental visits hard, there are ways to make the appointment easier. At Lumi we offer happy gas (nitrous oxide), inhaled pain relief, oral sedation and IV sedation for suitable patients, and we are happy to talk about which might suit you at your consult. We do not provide general anaesthetic.
How long a crown can be expected to last
Crowns are not permanent, but many serve for well over a decade. How long yours lasts depends on how well the gum line is cleaned, whether new decay starts at the edge, how hard you bite and grind, and what you chew. A night guard is often suggested for people who grind. Our article on what changes with a crown years later covers the slow changes to watch for, and tooth decay under a crown explains the most common reason one needs replacing.
Health funds and getting a quote you can compare
Most extras policies treat crowns as major dental, which often means a longer waiting period and a lower annual limit than for check-ups. Ask for a written treatment plan with fees that lists each item number before treatment starts. Your fund can then tell you exactly what it will pay, and you can compare like with like if you get a second opinion.
How we plan crowns at Lumi Dental
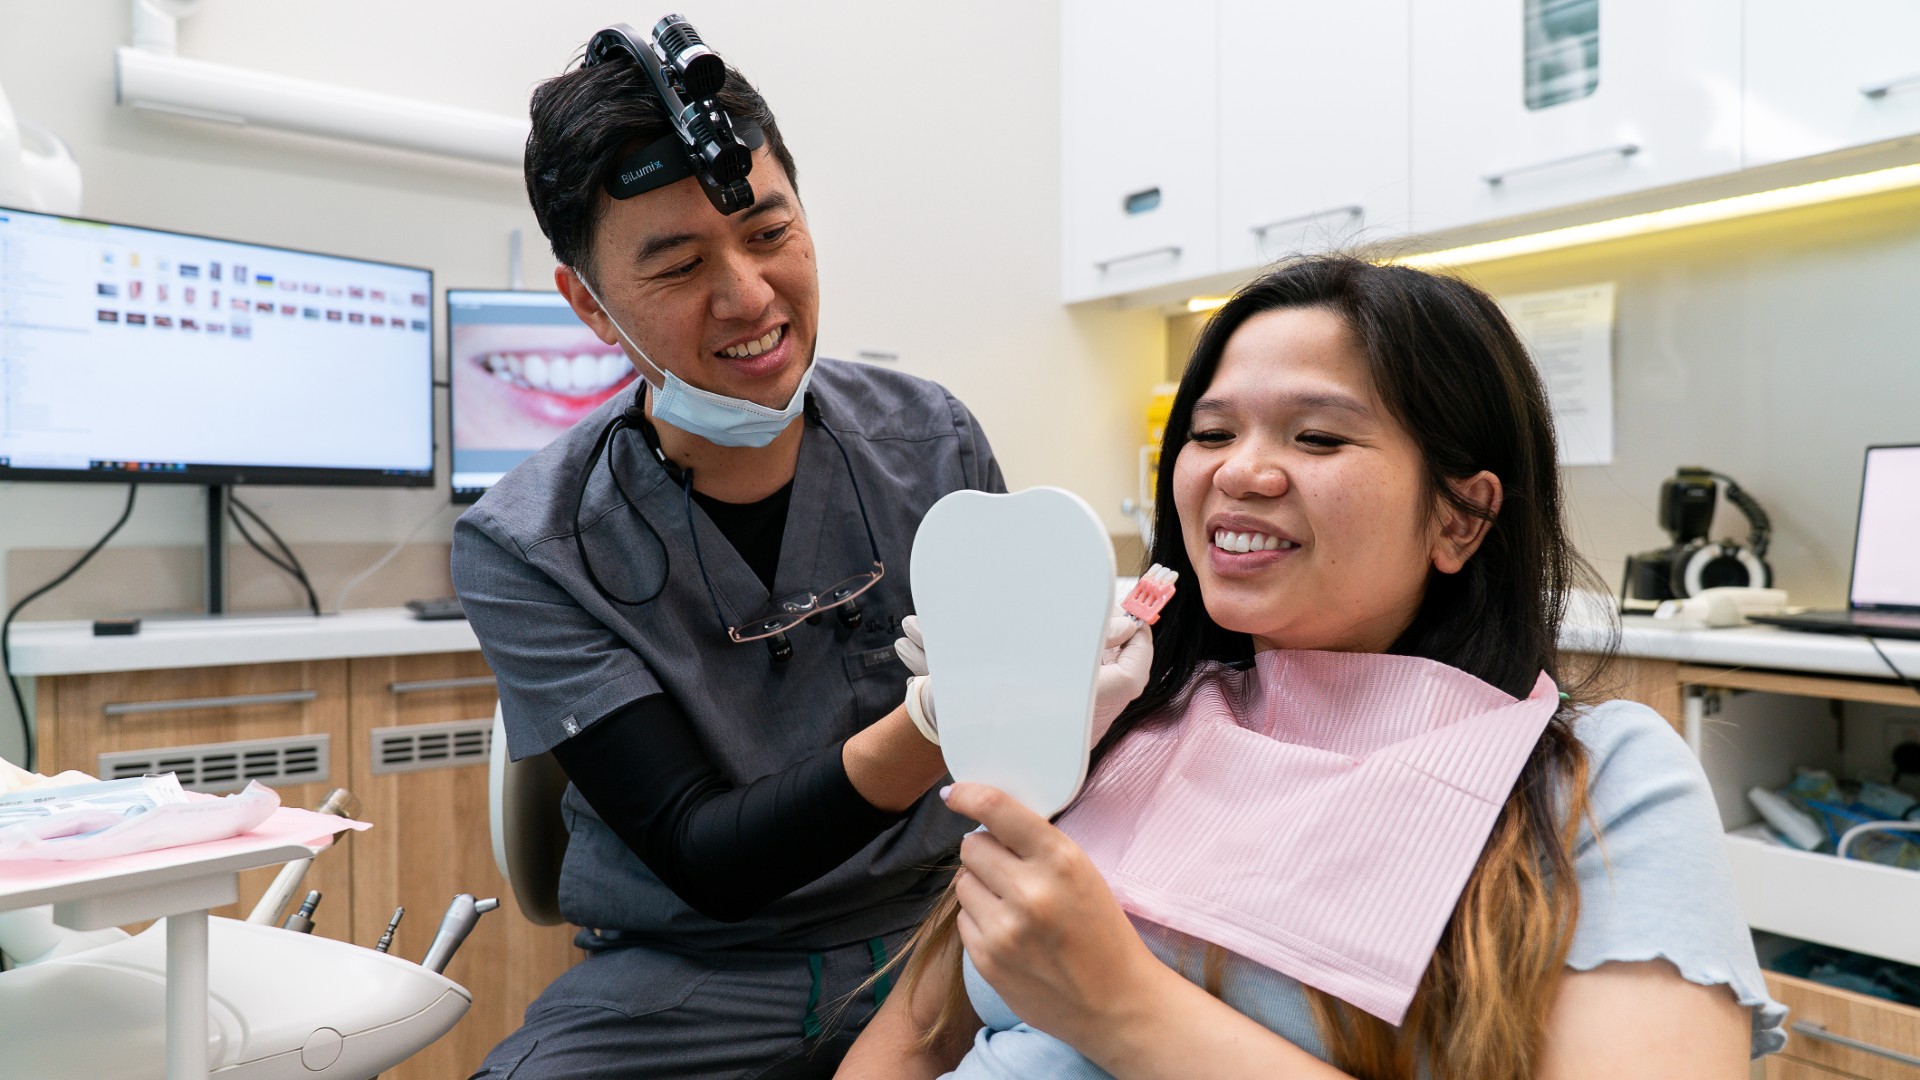
Before recommending a crown, we show you the X-rays and clinical photos the recommendation is based on and explain why a crown is suggested rather than a filling or onlay. You will usually receive a written treatment plan with item numbers and fees, often by email, before treatment is booked. We use a 3D intraoral scanner to record the prepared tooth, and the practice has its own in-house lab. We also claim health fund rebates on the spot through HICAPS.
Common questions
Is a crown better than a big filling?
Not always. A filling keeps more of the tooth, costs less and is the right choice when enough healthy tooth remains. A crown is suggested when what is left is too weak to rely on a filling.
How is a crown different from a veneer?
A veneer covers only the front surface of a tooth and is mostly cosmetic. A crown covers the whole tooth and is used when it needs protecting all the way round.
Can a crown be done in one visit?
Some practices offer same-day milled crowns. Whether that suits you depends on the tooth and the material that is best for it.
If you have been told you need a crown and would like a clear explanation of the options, read more about crowns and bridges at Lumi Dental in Melrose Park. We are open Monday to Saturday, until 9pm on Thursdays, with free undercover parking at Melrose Central.
About the author
Dr James Tran is a general dentist at Lumi Dental in Melrose Central, Melrose Park. He holds a Bachelor of Dentistry (BDent) from the University of Sydney and a Graduate Diploma in Oral Implants, and is a Master of the International Congress of Oral Implantologists (MICOI). You can read more about his background and clinical philosophy at drjamestran.com.au.
This article is general information based on current clinical evidence and does not replace individual advice. Suitability, risks, and expected costs for any dental treatment should be assessed in person. All procedures carry risk, and outcomes vary between individuals.