Many parents first hear about a palatal expander at an ordinary check-up, when the dentist points out that the upper back teeth close inside the lower ones, or that the adult teeth look set to run out of room. The expander is a fixed appliance in the roof of the mouth that widens the upper jaw a fraction of a millimetre at a time. In a growing child it can widen the jaw at the level of the bone rather than simply tipping the teeth outwards, and that is the main reason dentists like to assess a narrow jaw early.
A narrow upper jaw shows up in a few different ways
The most common sign is a posterior crossbite, where one or more upper back teeth bite inside the lower teeth instead of just outside them. Some children also slide the lower jaw to one side to find a comfortable bite. That shift may affect how the jaws and chewing muscles develop over years of growth, although good long-term studies are limited. Others have no crossbite at all but a narrow, crowded upper arch with too little space for the adult canines and premolars still to come.
Breathing sometimes comes into the conversation too. Widening the upper jaw also widens the floor of the nose, and in selected children who have been assessed with their GP or an ear, nose and throat surgeon, that can be part of a wider plan. An expander is not a treatment for snoring or sleep problems on its own. Our article on mouth breathing in children explains how those cases are worked up.
The widening happens along a seam in the middle of the palate
The upper jaw forms as two halves that meet along a line running front to back through the roof of the mouth, called the midpalatal suture. In young children the suture is a band of fibrous tissue rather than solid bone. When an expander pushes steadily outwards against the back teeth, the two halves can separate slightly at this seam, and over the following months new bone fills the space.
The midpalatal suture is not the only thing resisting the expander. The upper jaw is also joined to the cheekbones, nasal bones and skull base by a network of other sutures, and these stiffen as a child grows. Both factors explain why the same appliance produces more skeletal change in an eight year old than in a seventeen year old.
Age is a rough guide, not a deadline
It is often said that the palate "fuses" at a set age. The research does not support a clean cut-off. Through adolescence the edges of the suture interlock more and more tightly, and when bony bridging begins it usually starts towards the back of the palate. In a cone beam CT study, Angelieri and colleagues (American Journal of Orthodontics and Dentofacial Orthopedics, 2013) graded the suture in five stages, A to E. The early stages A and B were typical up to about 13 years of age, the intermediate stage C was seen mostly between 11 and 17 but occasionally in older people, and fusion was already present in some teenagers. An earlier study by Persson and Thilander (1977) found very wide individual variation in suture closure between the ages of 15 and 35.
So two children born in the same month can be at quite different stages. What is consistent is the direction of change: as the suture matures, a conventional expander anchored only on the teeth produces less bone widening and more tipping of the teeth. A dentist therefore looks at the bite, the stage of tooth development and general growth, and in some older patients a 3D scan, rather than relying on age alone.
Fitting the appliance and turning the screw
The expander is made from a scan or impression of the teeth. Most designs are held by metal bands or bonded attachments on the upper back teeth and cannot be taken out at home. A small screw sits in the centre, and a parent turns it with a key following a schedule set by the treating dentist or orthodontist. The active phase usually lasts a few weeks.
After a turn, children often feel pressure across the palate or up towards the nose for a short time. Extra saliva, a slight lisp and some awkwardness when swallowing are common for the first few days. Partway through, a gap usually opens between the two upper front teeth. It looks alarming to many parents but shows that the two halves of the jaw are moving apart, and it generally closes over the following weeks and months as the gum fibres draw the teeth back together.
Most of the treatment time is spent holding the new width
Once the planned width is reached, the turning stops but the expander stays in place, usually for several months. During this time new bone consolidates in the widened suture. Taking the appliance out too soon makes it more likely that some of the width will be lost.
Food collects easily around the bands and under the appliance. Careful brushing along the gum line, rinsing with water after meals and a water flosser all help, and very sticky or hard foods are best avoided because they can loosen a band. Regular reviews let the dentist check that the gums and teeth around the expander stay healthy.
Braces often follow, but not always straight away
An expander corrects the width of the jaw. It does not line up individual teeth, so many children go on to braces or aligners later, sometimes years later once the adult teeth have come through. Some only need the expander at this stage and are then monitored. How expansion fits with other bite problems is covered in our guide to overbite, underbite and crossbite, and if a baby tooth has been lost early, our article on space maintainers for children explains a different appliance that holds space rather than creating it.
Older teenagers and adults have other options
When the suture is more mature, a tooth-borne expander becomes less effective and more of the change comes from the teeth tipping outwards. For older teenagers and adults, two approaches can still widen the jaw itself. Bone-anchored expansion, often called MARPE, uses small miniscrews in the palate so the force is delivered to the bone rather than through the teeth. Surgically assisted expansion is another option in some cases. Lumi Dental places MARPE appliances for suitable adults, and our article on adult palatal expansion with MARPE explains who it may suit.

What an assessment with us involves
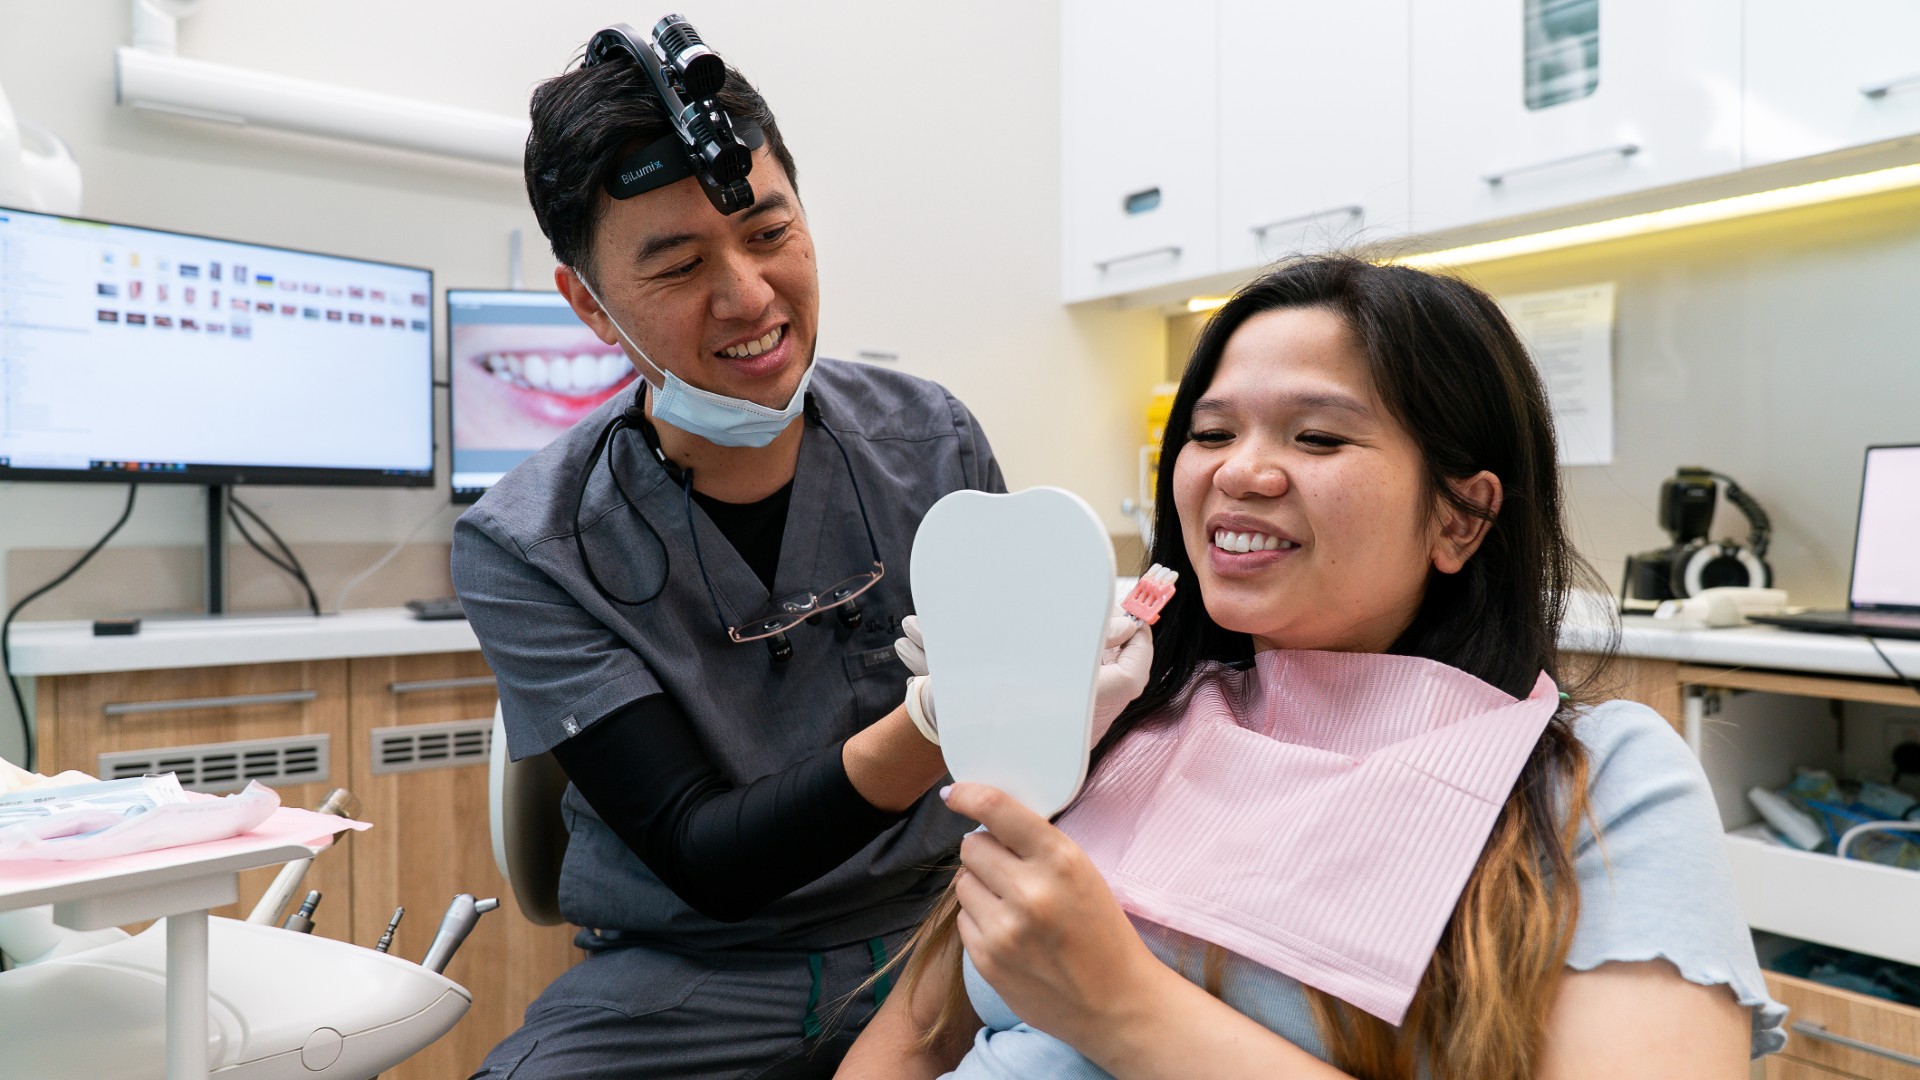
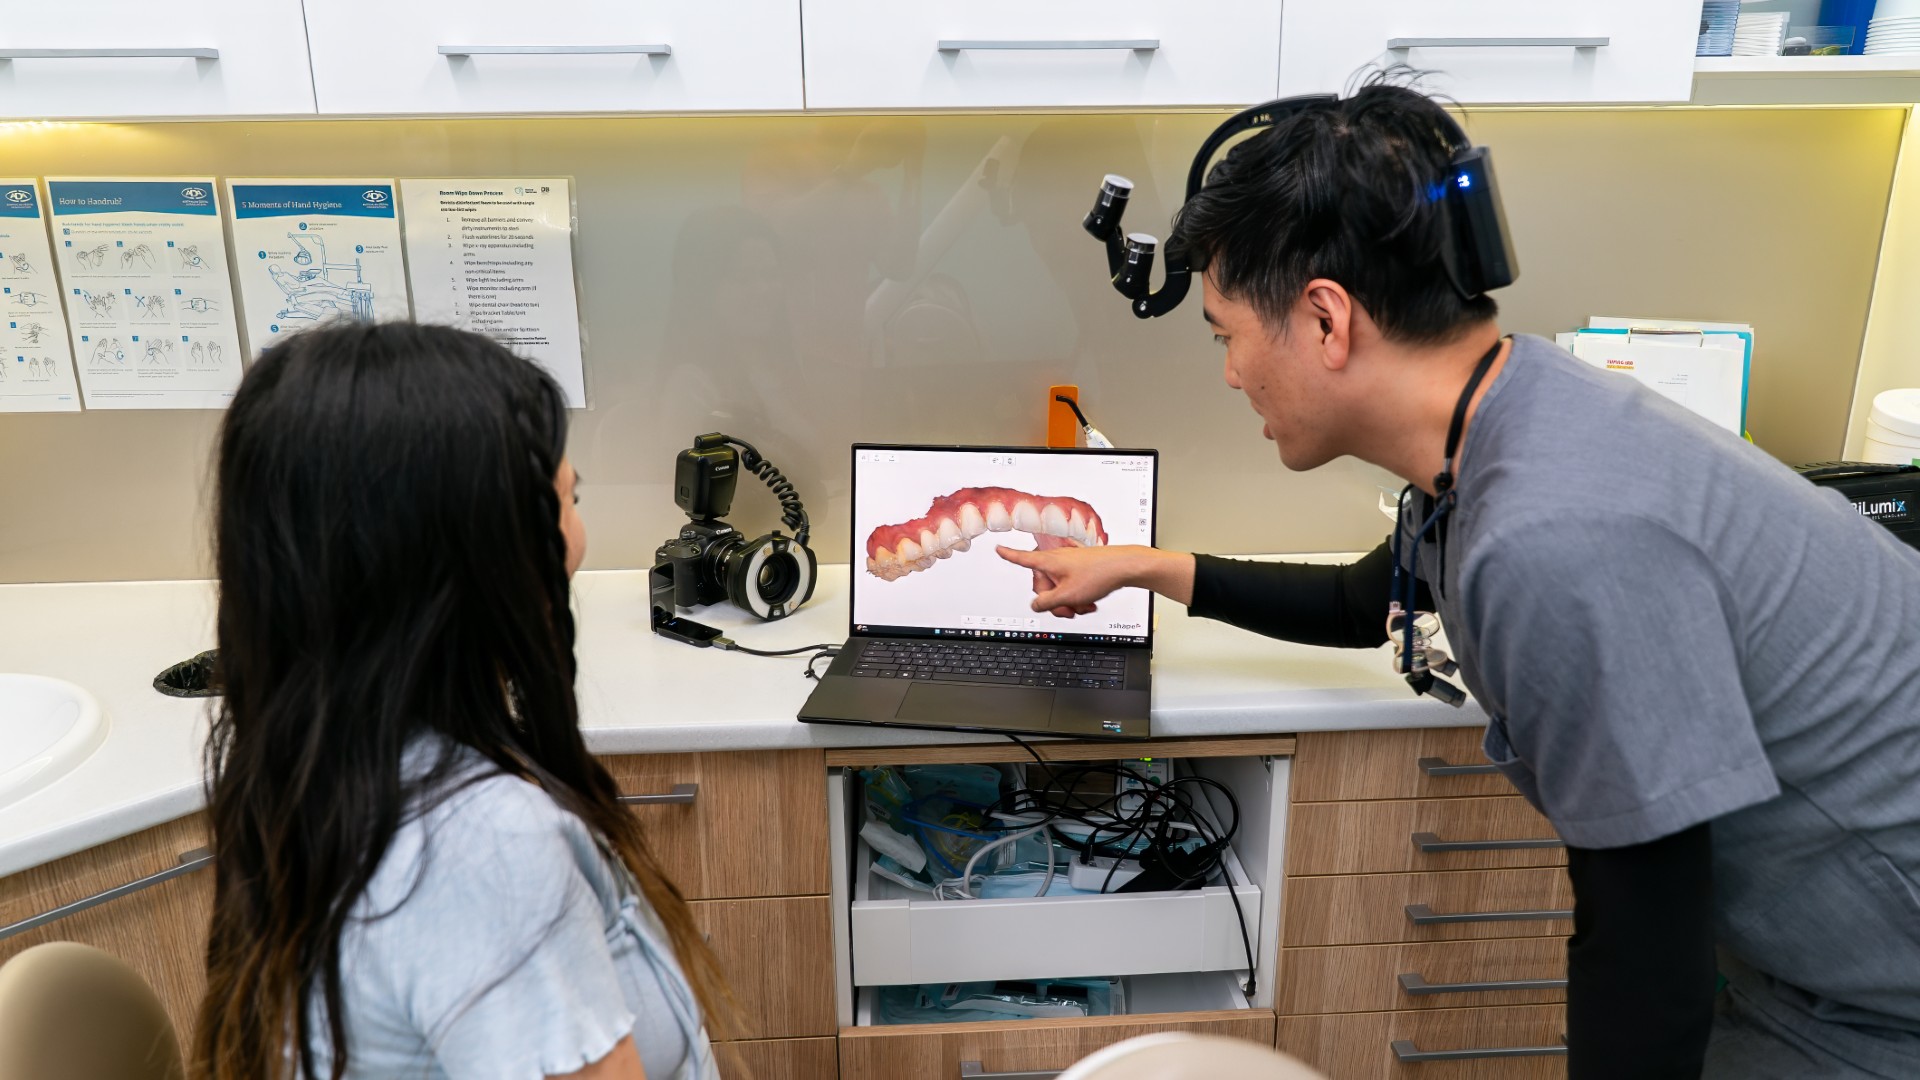
Our general dentists check how a child's teeth meet and how wide the upper arch is as part of their regular examinations. If expansion may help, we explain the findings with photos or a 3D scan of the teeth, talk through timing, and set out a written plan. For more complex orthodontic cases we refer to a registered orthodontist.
Because an expander is usually one stage of a longer plan, the only meaningful cost is a written treatment plan with fees after your child has been assessed. Some extras policies include orthodontic cover, depending on the fund and waiting periods. Our current deals page shows what is on offer at the moment.
Questions parents ask about expanders
Does a palatal expander hurt?
Most children describe pressure rather than pain, mainly in the minutes after a turn and over the first few days. If needed, over-the-counter pain relief at the dose on the packet is usually enough. Sharp or worsening pain should be checked by the treating dentist.
How long does the whole process take?
The turning phase is usually a few weeks, and the holding phase several months. Your dentist or orthodontist will give a timeline based on how much widening is planned.
When should a child first be checked?
The American Association of Orthodontists suggests an orthodontic check by about age 7. Regular dental visits from a young age, described in our guide to your child's first dental visit, mean bite problems are often noticed well before then.
If your child's upper teeth bite inside the lower ones, or you are worried about crowding, an assessment is a sensible next step. You can book a visit with the team at Lumi Dental, or look at our current options first.
This article is general information and not a substitute for personal dental advice. Outcomes vary between individuals.