
Studies have found that somewhere between about one in six and one in three of the people measured have upper and lower front teeth whose sizes are significantly out of proportion, with the figure depending on the group studied and how a significant mismatch is defined. Neither set is wrong on its own. The mismatch mainly shows when the two arches meet, and if it is not planned for, it can make it harder to close small gaps or to get the front teeth to fit together well at the end of straightening.
Upper and lower teeth are meant to be in proportion
For the upper and lower front teeth to fit together with a normal overlap and no spaces, the combined width of the lower teeth needs to be in a fairly steady proportion to the combined width of the upper teeth. Clinicians measure this as a percentage, known as the Bolton ratio after Bolton, who developed it from a study of 55 people with excellent bites.
A 2020 meta-analysis by Machado and colleagues (Journal of Orthodontics) pooled 53 studies and 11,411 people. In people with a normal bite, the six lower front teeth, canine to canine, were on average about 78% of the width of the six upper front teeth (78.25%). Measured from first molar to first molar, the lower teeth were about 92% of the upper (91.78%). These averages differ slightly from the values Bolton originally published, which suggests his figures are best treated as a guide rather than a fixed target.
When the ratio sits well away from the average, one arch has relatively more tooth width than the other. Once the teeth are aligned, this can show up as spaces that are hard to close, or as front teeth that do not overlap in a normal way.
How common a significant mismatch is
Figures vary with the population studied and with how "significant" is defined. A literature review by Othman and Harradine (Journal of Orthodontics, 2006) found studies reporting significant discrepancies in the front teeth in 20% to 30% of people, and across the whole arch in 5% to 14%. Some individual studies:
| Study | Who was measured | Front teeth outside 2 standard deviations |
|---|---|---|
| Santoro and colleagues, Angle Orthodontist, 2000 | 54 Dominican Americans | 28% (overall arch 11%) |
| Othman and Harradine, Angle Orthodontist, 2007 | 150 white orthodontic patients | 17.4% (overall arch 5.4%) |
| Ajami and colleagues, Electronic Physician, 2018 | 150 orthodontic patients in Iran, aged 17 to 28 | 34.7% (overall arch 20.7%) |
Bernabé and colleagues (American Journal of Orthodontics and Dentofacial Orthopedics, 2004) measured 200 Peruvian adolescents with no previous orthodontic treatment and found clinically significant discrepancies in almost a third of the sample.
Sex and ethnic background seem to make little clinical difference to the ratios. Othman and Harradine concluded that neither was likely to have a clinically significant effect, and Machado and colleagues found sex had almost no effect on the proportions. Bite type showed more of a pattern: the meta-analysis found people with a Class III bite, where the lower jaw sits further forward, tended to have proportionally larger lower teeth.
Small upper lateral incisors can play a part
The upper lateral incisors, either side of the two upper front teeth, are sometimes small or peg-shaped. Ajami and colleagues tested a quick visual comparison of the upper and lower lateral incisors and found it picked up 96% of significant front tooth discrepancies in their sample, although it also flagged many people who did not have one. In that sample, most front tooth discrepancies involved relatively large lower teeth rather than small upper ones. Where an upper lateral is small, it can leave the upper arch short of tooth width, so spaces may remain beside it once the teeth are aligned.
The canines are part of the picture too. In adults examined at age 46 in the Northern Finland Birth Cohort 1966 who had not had orthodontic treatment, Turtinen and colleagues (Acta Odontologica Scandinavica, 2021) found that very large overjet (8 mm or more), where the upper teeth sit well forward of the lower, and reverse overjet were both associated with tooth size discrepancy at a population level, with the widths of the upper canines and incisors linked to the overjet.
A small lateral can also affect how a smile looks before any straightening, because the proportions between the front teeth change. Our articles on peg-shaped lateral incisors and on tooth width proportions in smile design look at that side of it.
Measuring is more reliable than looking
Othman and Harradine suggested that a size difference needing more than 2 mm of correction is a reasonable threshold for clinical significance. Endo and colleagues (Angle Orthodontist, 2009) reached a similar conclusion in 250 sets of models, recommending both the ratio and the actual millimetres be considered. In their 2007 study, Othman and Harradine found visual estimation of a discrepancy had low sensitivity and specificity and concluded careful measurement is needed more often than looking alone would suggest. Ajami and colleagues reported that visual screening picked up most discrepancies in their sample but also produced many false alarms (sensitivity 96%, specificity 34%), and they still recommended routine measurement.
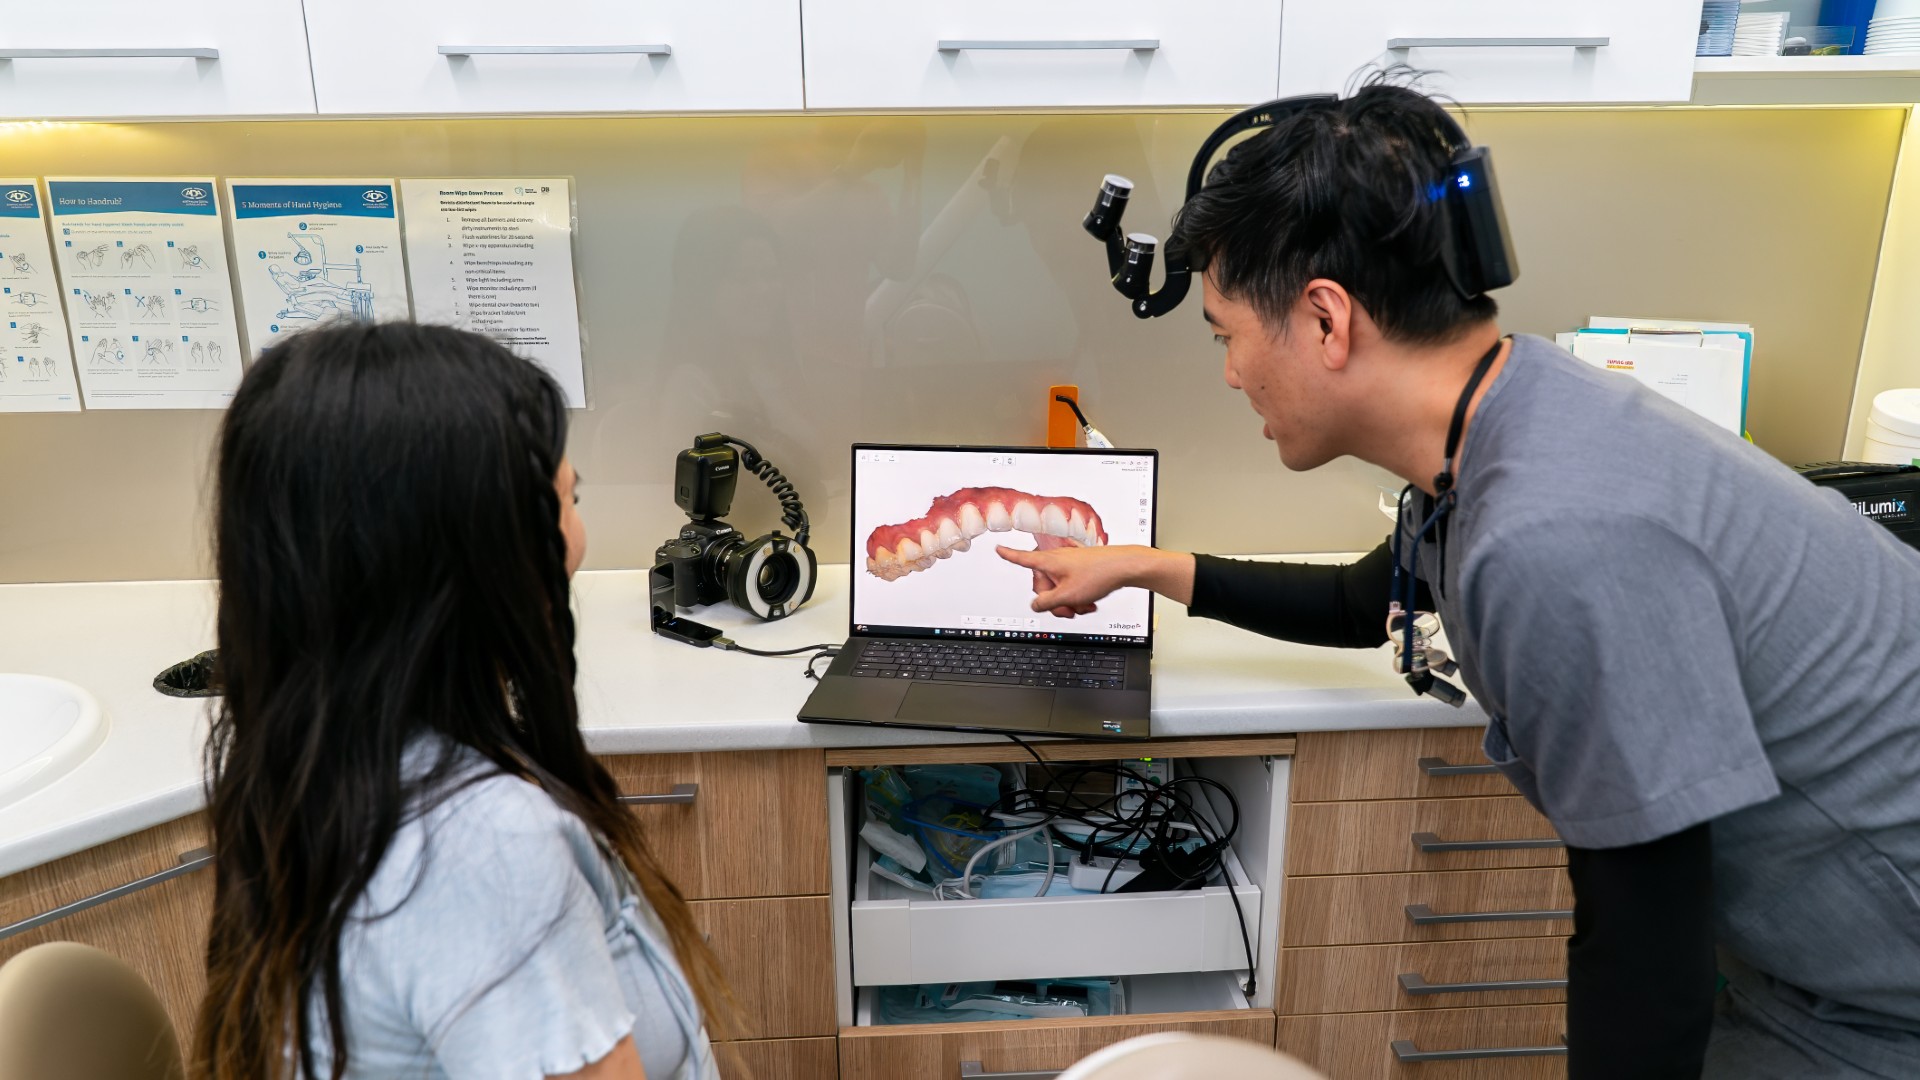
Tooth widths can be measured on models or on a digital scan. At Lumi, teeth are recorded with a 3D intraoral scanner. Finding a mismatch at the start means it can be planned for, rather than discovered as a stubborn gap near the end of treatment.
Ways a size mismatch can be managed
The aim is to balance the tooth width between the arches. That can be done by taking a little width from the arch with too much, or adding width to the arch with too little. Which suits you depends on the size and position of the discrepancy, the health of the teeth and how you want your smile to look.
| Approach | When it may suit | Things to weigh |
|---|---|---|
| Reshaping between teeth (interproximal reduction) | The arch with relatively large teeth, such as the lower front teeth | Removes a small, measured amount of enamel that does not grow back |
| Adding composite bonding to small teeth | Small or peg-shaped upper lateral incisors leaving spaces | Adds width without removing much tooth; bonding may need repair or replacement over time |
| Porcelain veneers or crowns on small teeth | When shape and colour also need to change | Usually involves some tooth preparation; a longer-term restorative commitment |
Reshaping between teeth is also used to create space when straightening crowded teeth, including with aligners, and our guide to attachments and IPR explains how it is done. On safety, a systematic review by Koretsi and colleagues (Orthodontics and Craniofacial Research, 2014) found no difference in decay between reshaped and untouched surfaces from one to seven years afterwards. A later review by Gómez-Aguirre and colleagues (Orthodontics and Craniofacial Research, 2022) also found no increase in decay, gum changes or sensitivity, while rating the quality of the evidence as low to very low.
When the upper laterals are the small teeth, adding width to them is an option. Miyajima and colleagues (Journal of the Canadian Dental Association, 1993) described using porcelain veneers after orthodontic treatment where small lateral incisors had caused a size discrepancy between the arches. Composite bonding can also be used to add width, usually with little or no tooth removed.
Why the order of treatment matters
When a smile needs both straightening and added width, the teeth are often moved first and then built up, with spaces left beside the small teeth so bonding or veneers can bring them to a natural width. Planning this together from the start avoids closing a space that will later be needed. If the plan does not allow for a size difference, the result can be a gap that keeps reopening or a bite that does not quite settle. Our article on teeth shifting after orthodontic treatment covers the more common reasons teeth move once treatment ends, and our guide to aligner refinements explains why plans are sometimes adjusted partway through.
At Lumi, our dentists provide both clear aligners and fixed braces. We are general dentists, not orthodontists, and more complex cases may be referred to a registered orthodontist.
What people ask about mismatched tooth sizes
Is a tooth size discrepancy a problem if my teeth are not being straightened?
Often not. It matters most when teeth are being moved, or when bonding or veneers are planned, because that is when the two arches need to fit together in a new position.
Can aligners close every gap?
Aligners can close spaces, but they cannot add tooth material. If the upper teeth are simply too narrow for the lower ones, a gap may only close at the cost of the bite, so the plan may instead leave space for bonding.
Will reshaping between my teeth make them sensitive?
The reviews above did not find more sensitivity or decay after reshaping, although the evidence is limited. The amounts removed are usually small and planned for each contact.
Thinking about straightening or reshaping your teeth?
A consultation for aligners, braces or cosmetic treatment at Lumi is free, and it is a chance to ask whether size differences between your teeth may affect your plan. See our current offers or book a consultation at our practice in Melrose Park.
Sources
- Machado V, Botelho J, Mascarenhas P, Mendes JJ, Delgado A. A systematic review and meta-analysis on Bolton's ratios: normal occlusion and malocclusion. J Orthod. 2020;47(1):7-29. PubMed 31718451
- Othman SA, Harradine NW. Tooth-size discrepancy and Bolton's ratios: a literature review. J Orthod. 2006;33(1):45-51. PubMed 16514133
- Othman S, Harradine N. Tooth size discrepancies in an orthodontic population. Angle Orthod. 2007;77(4):668-674. PubMed 17605478
- Santoro M, Ayoub ME, Pardi VA, Cangialosi TJ. Mesiodistal crown dimensions and tooth size discrepancy of the permanent dentition of Dominican Americans. Angle Orthod. 2000;70(4):303-307. PubMed 10961780
- Bernabé E, Major PW, Flores-Mir C. Tooth-width ratio discrepancies in a sample of Peruvian adolescents. Am J Orthod Dentofacial Orthop. 2004;125(3):361-365. PubMed 15014416
- Ajami S, Fattahi H, Zare M, Jenabi P. Bolton discrepancy in an Iranian population and its relation with maxillary lateral incisors' size. Electron Physician. 2018;10(3):6454-6461. PubMed 29765569
- Turtinen H, Sarja M, Hyvärinen J, et al. Associations between Bolton ratio and overjet deviations in a Finnish adult population. Acta Odontol Scand. 2021;79(8):593-599. PubMed 33896362
- Endo T, Uchikura K, Ishida K, et al. Thresholds for clinically significant tooth-size discrepancy. Angle Orthod. 2009;79(4):740-746. PubMed 19537863
- Koretsi V, Chatzigianni A, Sidiropoulou S. Enamel roughness and incidence of caries after interproximal enamel reduction: a systematic review. Orthod Craniofac Res. 2014;17(1):1-13. PubMed 24011354
- Gómez-Aguirre JN, Argueta-Figueroa L, Castro-Gutiérrez MEM, Torres-Rosas R. Effects of interproximal enamel reduction techniques used for orthodontics: a systematic review. Orthod Craniofac Res. 2022;25(3):304-319. PubMed 34865310
- Miyajima K, Shirakawa K, Senda A. Application of porcelain veneers following orthodontic treatment. J Can Dent Assoc. 1993;59(2):167-170. PubMed 8453519
This article is general information only and is not a substitute for advice about your own situation from a dentist.