Most people speak clearly with a new full-arch implant bridge within a few weeks, but a lisp on s and z, a faint whistle, or air and saliva escaping under the bridge are common in the first days, and they come from two things: a tongue learning new landmarks, and a bridge whose shape still needs tuning. Speaking with a new full-arch implant bridge differs from speaking with a denture: there is no palate to adapt to, but a small gap between the bridge and the shrunken gum can let air through. In an acoustic study of 34 people with upper fixed implant bridges, nine of twelve consonants differed from people with natural teeth before treatment and three of twelve afterwards.
Written by Dr James Tran, BDent (University of Sydney), MICOI, GradDip (Oral Implants), general dentist at Lumi Dental in Melrose Park.
The short version
- A fixed bridge has no palate and no flange, so denture clicking goes, and a new problem appears: air or saliva slipping under the bridge.
- The sounds that change are s, z, f, v and th; most settle within a few weeks with normal talking and reading aloud.
- The provisional acrylic bridge is where speech is tuned: tooth position, the contour behind the front teeth and the junction with the gum can all be changed before the final bridge is made.
- A consensus report on the toothless upper jaw suggests an interim fixed prosthesis to check phonetics before the definitive one.
- A lisp or whistle not improving week on week by about week four is a shape issue to adjust, not something to practise through.
- Long-term denture wearers should also read speaking with new dentures; some habits carry over.
Why a fixed bridge sounds different from a denture
Speech is shaped by the tongue touching the teeth, the ridge behind them and the palate. A complete upper denture covers the palate and runs a flange under the lip; a fixed bridge has neither. A consensus report on the toothless upper jaw in Clinical Oral Implants Research explains that a fixed implant bridge is made without flanges so it can be cleaned underneath, which means no flange to support the lip and no palatal extension to help speech where a lot of bone has gone.
Where the ridge has shrunk, a channel can open between the bridge and the gum; air pushed forward for an s or an f escapes through it, and saliva collects there and sprays on a hard consonant. The provisional adds a second factor: acrylic has to be thicker than zirconia for strength, and the bulk behind the front teeth crowds the tongue exactly where s and z are formed.
The sounds that change, and what each one tells the dentist
Each awkward sound points to a part of the bridge. In the chair I ask patients to count from sixty to seventy, say "fifty-five" and read a sentence full of th sounds, because each tests a different contact.
| Sound | What you notice | Likely cause | What is adjusted |
|---|---|---|---|
| s and z | Lisp, slushy or whistling s | Tongue tip has lost its landmark; contour behind the front teeth too thick or thin | Palatal contour, front tooth position and length |
| f and v | Soft or muffled; lower lip cannot find the edge | Upper front teeth too short, long or far in | Length and angle of the upper front teeth |
| th | Tongue catches or air hisses | Front teeth too far back or bridge too thick behind them | Thinning the bridge behind the incisors |
| Any hard consonant | Saliva spray or a wet sound | Gap under the bridge pooling saliva; extra saliva in the first days | Reshaping the junction with the gum; time |
| General | Whistle when talking | Narrow air channel under the bridge or between front teeth | Opening the channel or filling the gap |
The acoustic study above found that the distortions remaining after six months were in consonants made with the tongue just behind the front teeth, and the authors suggest an unsuitable palatal shape or an abrupt junction between bridge and shrunken bone as the reasons. The sounds that persist depend on bridge shape, and shape can be changed.
How long it takes
For most people the strange feeling eases within days and speech is close to normal within two to four weeks. NHS patient guidance for new dentures makes the same point: speech may be altered at first, settles within a few weeks, and reading aloud speeds it up. Fixed bridges follow a similar curve, with one difference I see: people who go straight from failing teeth to a bridge adapt fastest, while long-term denture wearers take longer because their tongue learnt to work against a palate.
A lisp that is clearly better each week is adaptation. A lisp that is the same in week four as in week one is a design matter for the next review, which is scheduled anyway while the implants heal; our full-arch implant treatment timeline shows where those reviews fall.
The provisional bridge is where speech is tuned
A fixed provisional bridge is worn for months while the implants fuse with the bone, and that period is a working trial. The consensus report suggests an interim fixed prosthesis to evaluate aesthetics, function, phonetics, occlusion, cleanability and soft tissue stability before the final prosthesis, so changes can be built into the definitive bridge. Acrylic can be added to and ground back in minutes; zirconia cannot.
A technique paper in the Journal of Prosthetic Dentistry describes the palatogram method for this problem: a marking paste is painted on the palatal side of the acrylic interim bridge, the patient speaks, and the pattern of tongue contact shows where the contour needs building up or thinning. The tuned interim bridge is then copied to make the definitive zirconia bridge. At this stage the dentist can also lengthen, shorten or reposition the front teeth, reshape the transition zone where the pink part meets the gum, and add or thin material where air escapes. Our guide to zirconia versus acrylic full-arch bridges explains why the final material is harder to adjust.
Practice that helps
Talk more, not less. Read aloud for ten minutes a day, slowly at first. Count from sixty to seventy, which is full of s sounds, and repeat words with f and v at the start and end. Record a voice message on day one and each week after; improvement is easier to hear than to feel. Swallow before a sentence to clear saliva, and speak a little slower for the first fortnight. Eating follows the same learning curve; see our guide to eating with a provisional full-arch bridge.

The single rule: if it is not improving week on week by week four, book an adjustment
Adaptation is a slope; a design problem is a plateau. The signs that point to the bridge rather than the tongue are a whistle on particular words every time, a lisp that got worse after a change to the bridge, saliva spraying in the same spot, or air you can feel under the bridge on "fifty". The provisional exists so these can be fixed before the final bridge is milled.
Almost all speech trouble comes from the upper bridge, because s, f, v and th are made against the upper front teeth and the ridge behind them. A lower bridge affects speech far less, though a bulky lower provisional can crowd the tongue for a week or two; see upper versus lower full-arch implants.
How we approach this at Lumi Dental
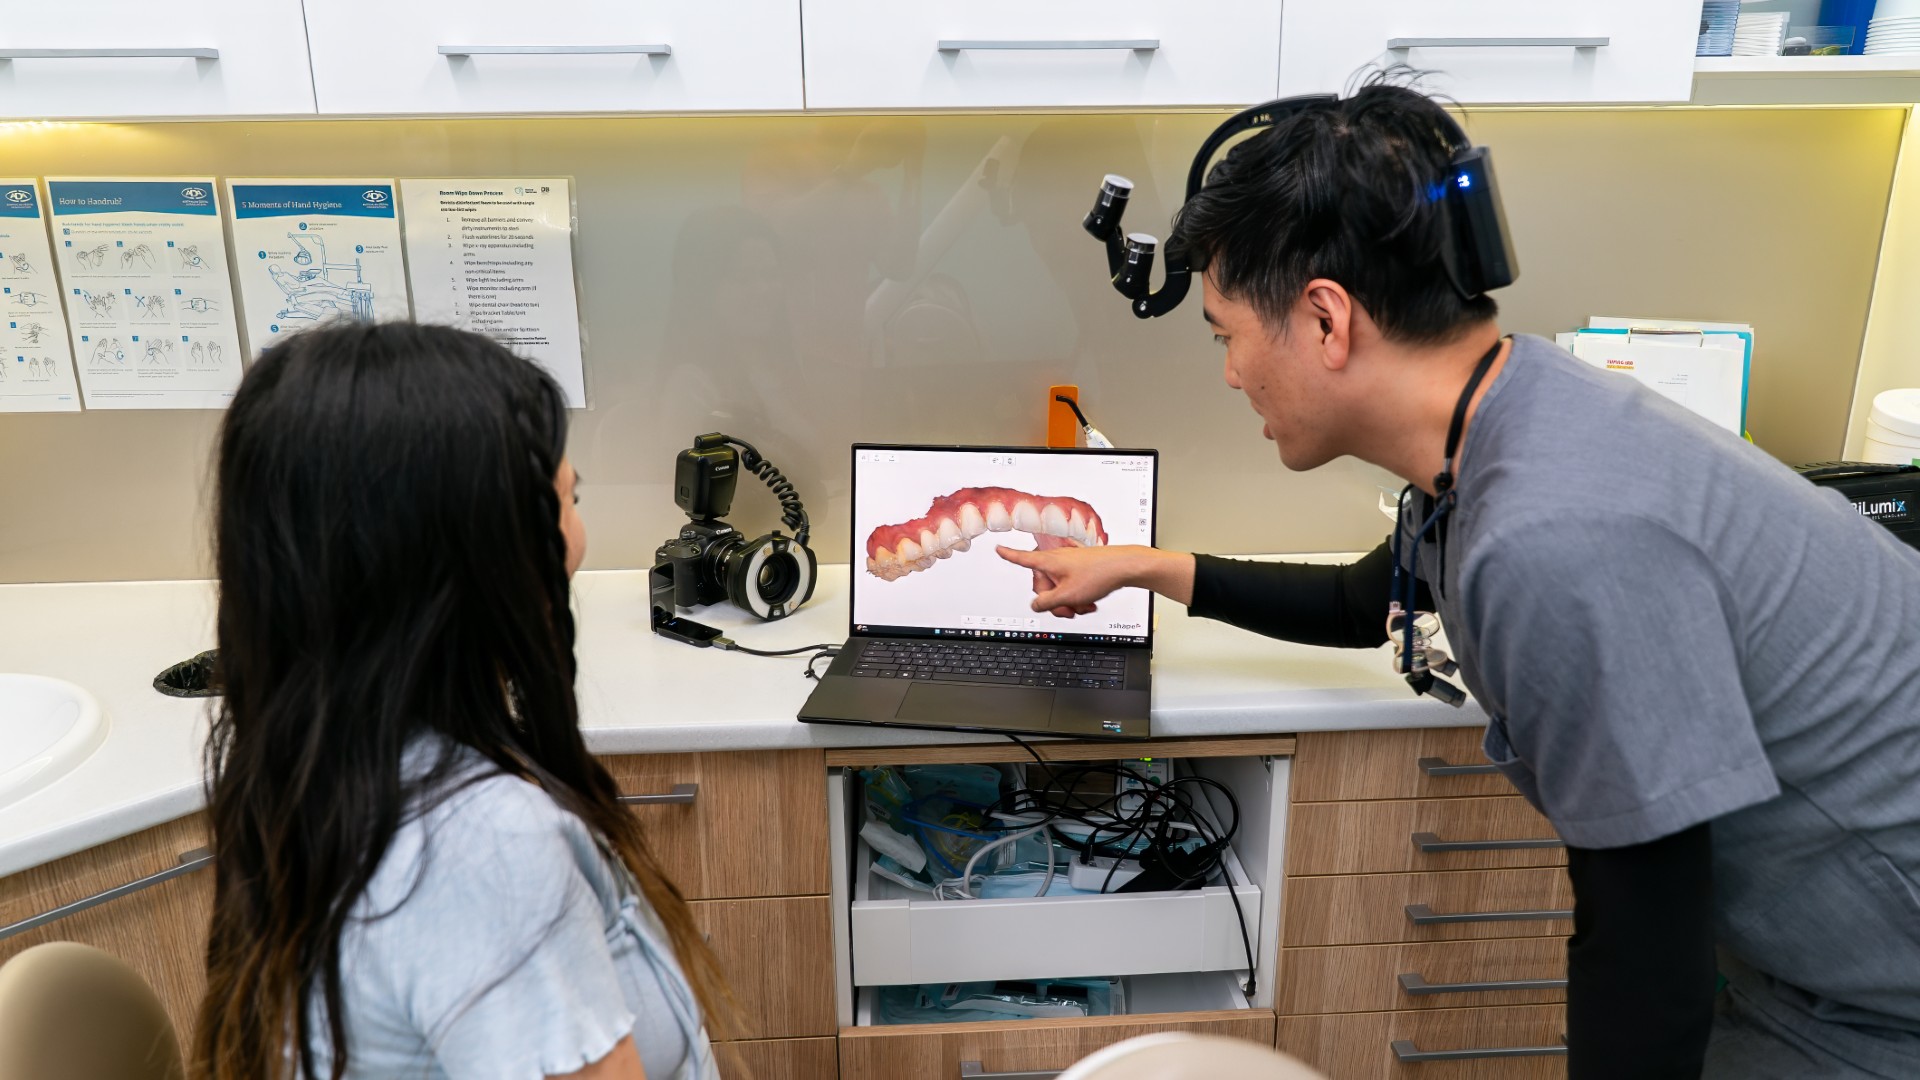
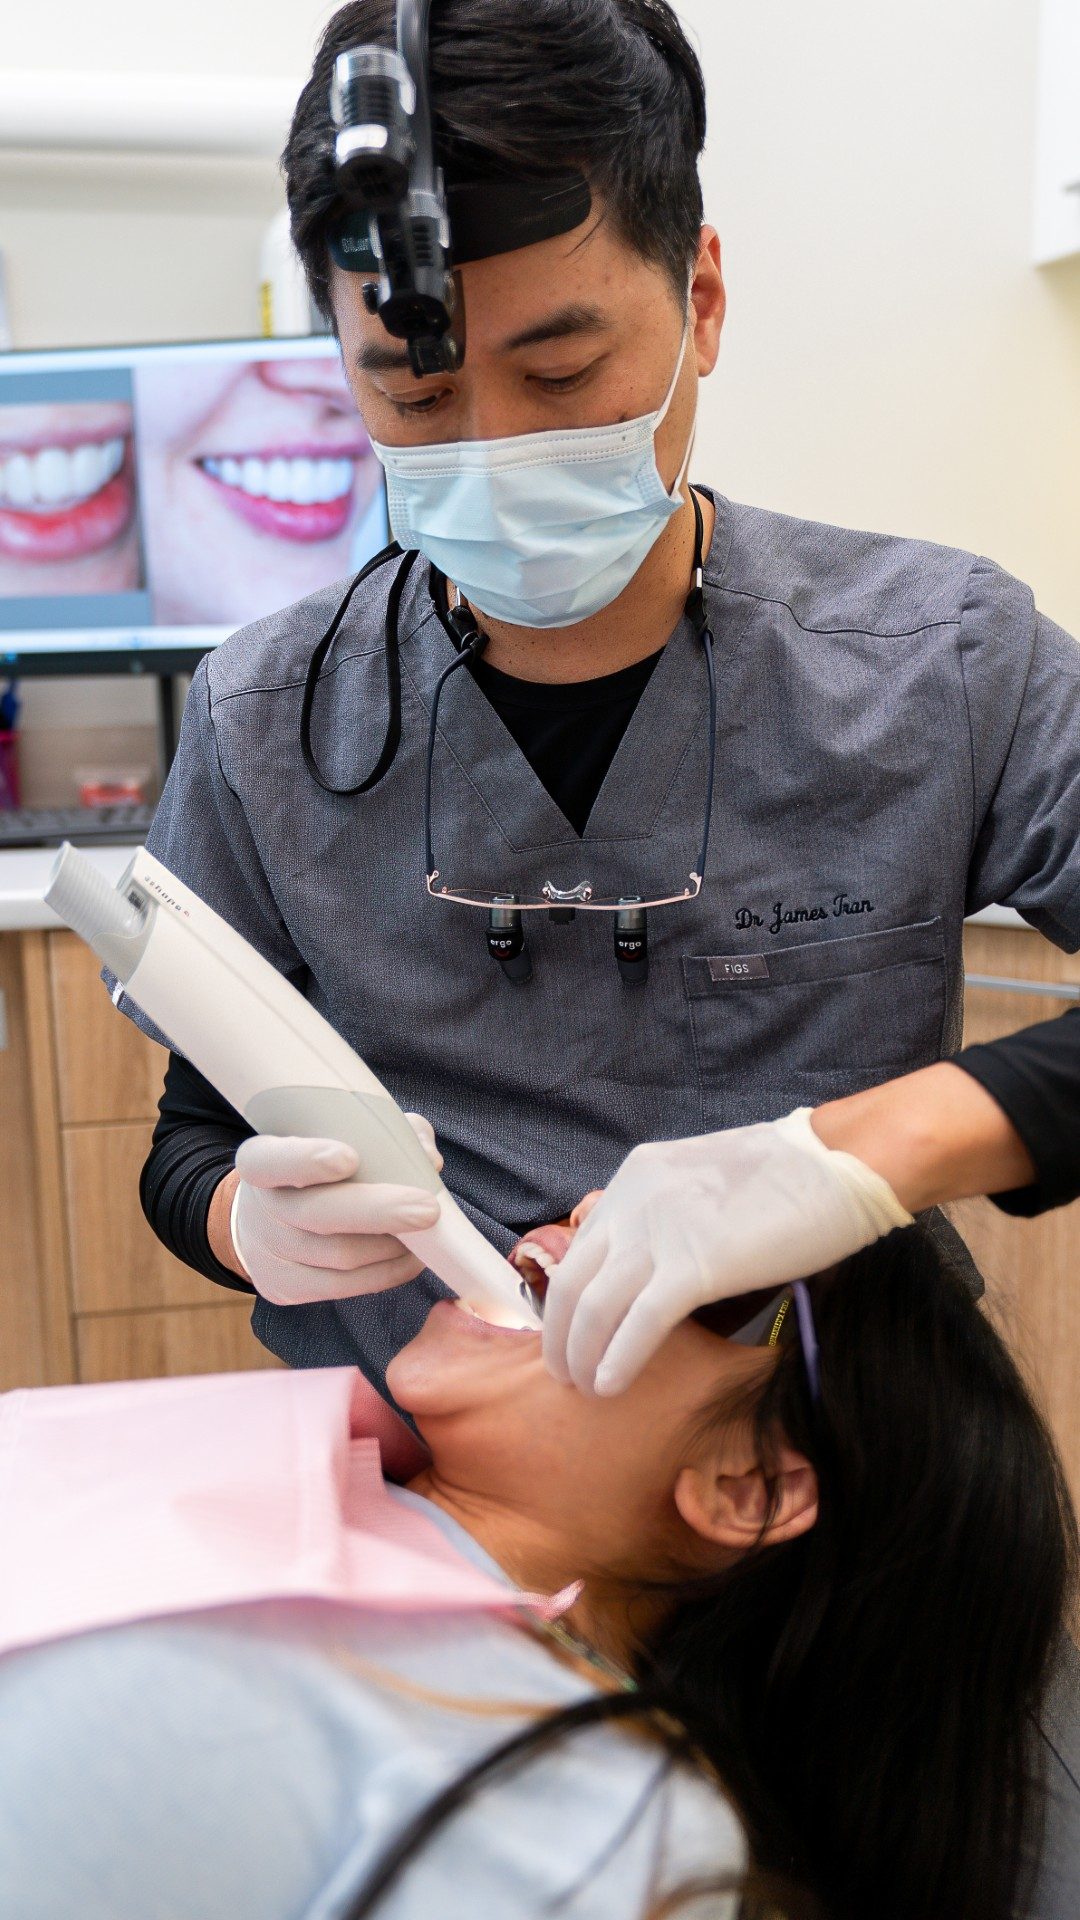
Lumi Dental in Melrose Park provides full-arch implant treatment under the name All-on-X, with in-house 3D intraoral scanning, 3D X-ray (OPG or CBCT) and 3D printing used in planning and in making the provisional bridge. Speech is checked at the provisional fitting and at each review while the implants heal, with the acrylic adjusted before the final bridge is designed. IV sedation is available for the surgical appointment. All-on-4 is a treatment concept trademarked by Nobel Biocare; see All-on-X versus All-on-4 and the service page for All-on-X full-arch implants at Lumi Dental.
Questions patients ask
Will I have a lisp with a full-arch implant bridge?
Possibly for the first week or two, mainly on s and z. For most people it fades with normal talking and reading aloud; one not improving by about week four is usually a contour matter to adjust on the provisional.
Why does air or spit escape under my bridge when I talk?
Because the gum has shrunk where the teeth used to be, and a fixed bridge cannot carry the sealing flange a denture has. The space can be reshaped on the provisional, and the extra saliva of the first days settles on its own.
Will the final zirconia bridge feel different to speak with?
Usually slimmer, because zirconia is stronger than acrylic and can be made thinner. If the provisional has been tuned and copied, speech is normally the same or better; a final bridge that introduces a new lisp should be reviewed.
Can speech still be fixed after the final bridge is made?
Small changes to the gum-facing surface and tooth edges are possible, but zirconia is difficult to add to, so a larger change means remaking.
Is speech better with a fixed bridge or a removable implant denture?
It varies. In a small crossover trial cited in the consensus report, 13 patients who tried both rated the removable implant denture higher for speech and cleaning, and nine chose to keep it; other studies report patients preferring fixed teeth. Where a great deal of bone has gone, a flange may give clearer speech.
Planning full-arch implants, or adjusting to a new bridge? Complimentary implant consult in Melrose Park
If you are weighing up full-arch implants, or have a new bridge with a lisp or whistle that is not settling, the team at Lumi Dental in Melrose Park can check the bridge contour and plan any adjustment. Contact Lumi Dental to book, or read about dental implants at the practice. Patients visit from Ryde, Parramatta, Ermington, Rydalmere and nearby suburbs.
Sources
- PMC (Clinical Oral Implants Research): Consensus report of Group 4, Global Consensus for Clinical Guidelines for the Rehabilitation of the Edentulous Maxilla
- PubMed (Journal of Prosthetic Dentistry): Articulation distortion in individuals with complete arch maxillary implant-supported fixed dental prostheses
- PubMed (Journal of Prosthetic Dentistry): Application of the palatogram technique to improve speech with complete-arch fixed implant-supported zirconia prostheses
- Cambridge University Hospitals NHS: Denture care, looking after your dentures
About the author

Dr James Tran is a general dentist at Lumi Dental in Melrose Park. He holds a BDent from the University of Sydney and a Graduate Diploma in Oral Implants, and is a Member of the International Congress of Oral Implantologists (MICOI).
This article is general information only and is not a substitute for an examination and individual advice from a registered dental practitioner. Suitability for any treatment varies from person to person.